A diagnostics company usually celebrates the wrong milestone. The champagne comes out when the assay validates: the analytical performance holds, the clinical study reads out, the papers get accepted. That is a real achievement. It is also the moment a dangerous assumption takes hold, that the hard part is over. In diagnostics, a validated test is the starting line, not the finish. The market does not reward a better test. It rewards a test someone will pay for.
This is the gap that kills more diagnostics than bad science ever will. The graveyard is full of assays with excellent data and no path to getting paid. To see how it happens, follow one example the whole way down.
A Perfect Test That Nobody Covers
Consider a polygenic risk score for breast cancer. The science is genuinely strong. It combines hundreds of genetic variants with established clinical risk factors, it is validated in large cohorts, and in the populations where it has been best studied it outperforms the standard clinical model at flagging women who carry elevated risk but test negative for the usual high-penetrance mutations. Transferability across ancestries remains the field's hardest open problem, and any honest version of this test would say so. On the merits, it works. It answers a real question for a real population: the large majority of women who develop breast cancer without a known hereditary mutation.
And yet standalone polygenic risk scores in breast cancer have a documented history of commercial failure. Several launched over the past decade with credible data. Most quietly pivoted away. Not because the science was wrong, but because the science was never the binding constraint.
The Buyer You Forgot Is the Payer
Here is what the validation data does not tell you. In diagnostics, the person who benefits from the test is rarely the person who pays for it. A clinician orders it. A patient receives it. But a payer decides whether it gets reimbursed, and that decision governs everything downstream. If a test is not covered, the clinician hesitates to order it because the patient gets a surprise bill, the lab hesitates to run it because it cannot reliably bill for it, and adoption is capped at whatever slice of the market will pay cash out of pocket.
For our breast-cancer score, that ceiling is brutal. There is no dedicated coverage for standalone polygenic risk testing, and major payers classify it as investigational. Meanwhile the dominant competitor's version of the same score rides inside an already-covered hereditary-testing panel, so it inherits a reimbursement umbrella the standalone product simply does not have. That umbrella is narrower than it looks, since it reaches only patients who already meet the criteria for hereditary testing, but a narrow covered market beats a broad uncovered one every time. The result: a scientifically superior test, structurally confined to a cash-pay, concierge, and executive-health niche, a fraction of the population it was built to serve.
Validity Is Not Utility, and Payers Only Buy Utility
Most diagnostic companies generate two kinds of evidence and assume they are done. Analytical validity: the test measures what it claims to measure, accurately and reproducibly. Clinical validity: the measurement correlates with the condition or the risk. Both matter. Neither is what a payer is buying.
Payers, and the guideline bodies that shape their decisions, require a third thing: clinical utility. Does using this test change what the physician does, and does that change improve outcomes? A risk score that produces a number no one acts on differently is, to a payer, an expensive way to generate anxiety. For our example, the reimbursement door stays shut until there is prospective evidence that acting on the score, earlier imaging, intensified screening, a prevention conversation, actually changes outcomes, and until a guideline body writes that action into its recommendations. That is a multi-year, expensive body of work. It is also the work most companies skip, because it is slower and harder than running one more validation study.
The Cash-Pay Trap
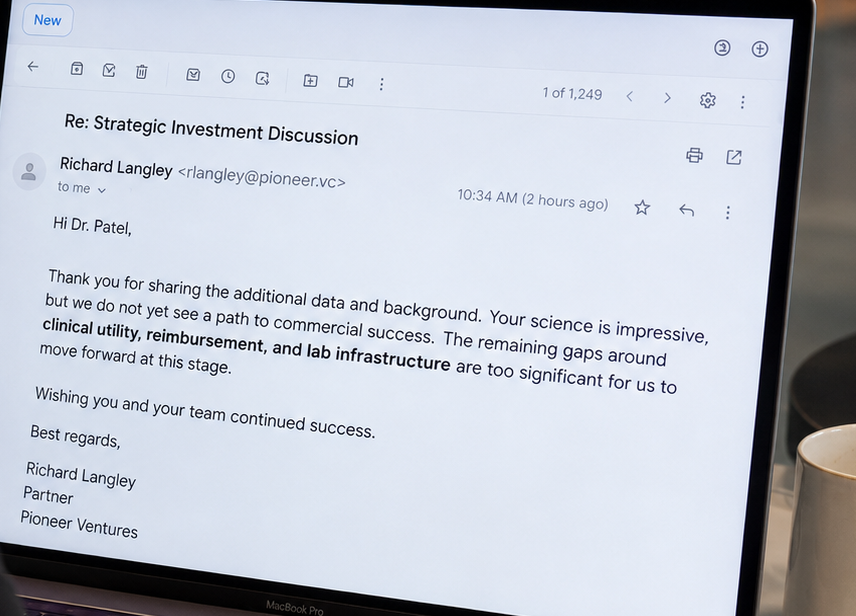
Faced with no coverage, companies reach for the same escape hatch: launch cash-pay now, sort out reimbursement later. Concierge medicine, executive health, direct-to-consumer. It feels like progress, because revenue is revenue. But cash-pay is usually a ceiling disguised as a beachhead. It generates just enough to look alive and never enough to scale, and it does nothing to build the coverage case. You cannot cash-pay your way to a payer policy. Without a deliberate plan to convert cash-pay traction into the evidence and coding that unlock reimbursement, you have not found a bridge. You have found the edge of your market.
Reimbursement Is a Clock You Start Late
The deepest problem is timing. A coverage pathway is not a switch you flip after launch. It is a multi-year sequence: generate clinical-utility evidence, secure a CPT code or navigate the gray zone of an existing one, win a coverage determination, which for molecular tests often runs through MolDX and the Medicare contractors, and earn the guideline inclusion that pulls commercial payers and clinicians along. Each step depends on the one before it, and each takes quarters or years.
If you start that clock at launch, you have already lost the window. The test is on the market, the burn is running, and coverage is still eighteen to thirty-six months away, if it comes at all. The companies that win designed the reimbursement strategy in parallel with the science, not after it. They knew the CPT path, the payer policies, and the guideline body's evidence bar before they finalized the product, and they built the clinical-utility study to clear that bar the first time.
Coverage Is Not Payment
There is a second trap waiting for the companies that clear the first one. Winning coverage feels like the finish line, and it is not. There are four gates, not two. Coverage decides whether the test is a benefit at all. Coding decides what you bill. Rate decides what the fee schedule pays. Collection decides what actually arrives in the bank.
Rate is the one founders model worst. For a molecular test, the price is set through the Clinical Laboratory Fee Schedule, either crosswalked to an existing code or sent to gapfill, where the Medicare contractors build a number from scratch. Gapfill routinely lands below the figure in the financial model, and once it is set it anchors commercial negotiations too, because payers do not pay a premium over Medicare without a reason. If your test is sole-source, Advanced Diagnostic Laboratory Test status lets you bill at your own list price for three quarters before the rate resets to the median private payer rate. Those three quarters are the most consequential pricing window in the product's life, and most teams arrive at them without a plan.
Collection is a gate again after that. A covered test, billed under the right code, at a published rate, still collects a fraction of that rate if the lab is out of network, if prior authorization is required and not obtained, or if denials go unappealed because nobody owns the appeals process. Coverage tells you the door is open. It does not tell you what is on the other side of it.
This is where established diagnostics companies get hurt, long after the science stopped being the question. Volumes hold, the tests are covered, and revenue per test drifts below plan until the model no longer works. It is a quieter failure than never getting covered at all, and for a company with public shareholders it is often a more expensive one.
The Public Version of This Problem
In July 2026, Myriad Genetics (NASDAQ: MYGN) gave the clearest public demonstration of this the industry has seen in years. Second quarter revenue came in at $190.7 million, down eleven percent year over year. Full-year guidance dropped to a range of $770 to $790 million. The stock fell roughly twenty-nine percent in a single session.
None of that was a coverage problem. The tests are covered. Demand for the hereditary cancer and mental health franchises was, in the chief executive's own words, solid. What moved was what the company actually collected per test.
Average revenue per test fell nine percent year over year across the business, and fifteen percent in hereditary cancer. Eleven million dollars came out of revenue from revised cash collection estimates on tests that had already been delivered in earlier periods. Another four million was written off as aged receivables in the mental health business. On the earnings call, management attributed the pressure to payer-initiated revenue cycle friction: changing prior authorization requirements, more frequent medical record requests, and higher denial rates. They were explicit that this was administrative burden rather than a change in medical policy.
That distinction is the entire argument of this piece. The policies did not change. The tests stayed covered. The clinical need stayed exactly where it was. The company still lost close to a third of its market value in a day, because the machinery between covered and collected got harder to operate. Management's own retrospective was that they should have engaged payers earlier.
If a company with three decades of payer relationships, a national contracting organization and a mature revenue cycle function can be repriced that hard by administrative friction, the lesson for a company at Series A is not subtle. Coverage is a milestone. Collection is the business. (Myriad Genetics Q2 2026 results.)
Reverse-Engineer From Coverage
The fix is a change in sequence, not effort. Start from the coverage decision and work backward. Which billing code will this test use, and does it exist yet? What do the relevant payer policies actually say about this category today? Which guideline body governs adoption, and what evidence does it require to include you? What is the clinical-utility study that would satisfy that bar, and can you run it before you launch rather than after? And what will this test actually be paid, built from a real fee schedule and a realistic collection rate rather than from a list price nobody has agreed to? Answer those questions first, and the commercial model, pricing, channel, and sales motion, sequences itself around when coverage is realistic. Skip them, and you will build a beautiful test that lives and dies in the cash-pay margins.
None of this diminishes the science. Great science is necessary. It is simply not sufficient, and treating it as the finish line is how good diagnostics die with their data intact.
The Bottom Line
Your assay validating is a genuine milestone. It is just not the one that decides whether the company succeeds. The test that reaches patients at scale is almost never the best test. It is the test with a coverage path, built in from the beginning. Getting the science right earns you the right to start. Getting paid is the part that decides how it ends.
Back to Blog